What the Music Is Doing
Music therapy can lower stress hormones and lift mood, the piece concludes, and it works best as a complement to other treatment.
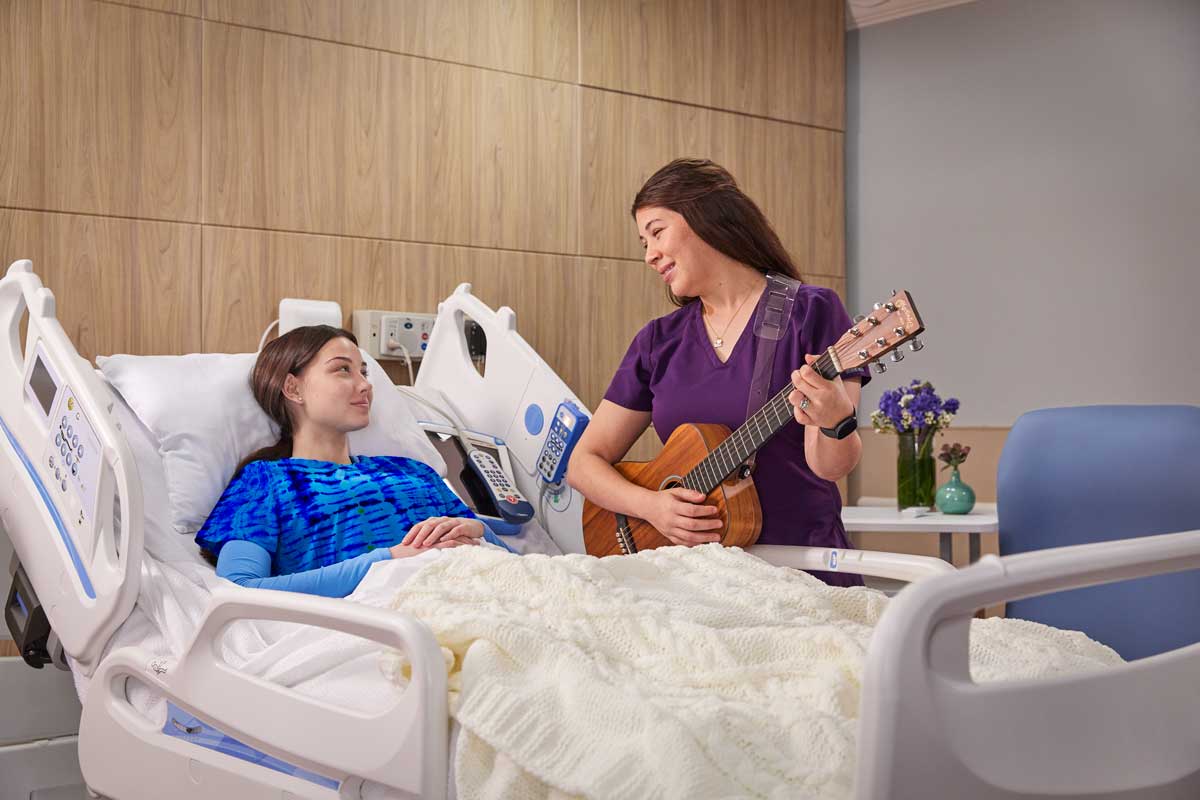

FOR as long as there have been people, music has changed how they feel. It can relax you, excite you, make a heavy day temporarily lighter, or absorb you completely. Most of us have put on a song to make a bad day better. But what happens when music is used deliberately, by a trained professional, to change how someone feels?
What Music Therapy Actually Is
Music therapy is the planned use of music by a trained, qualified therapist to work towards a health goal, with patients listening to or making music together with that therapist. It is not the same thing as putting on a playlist, and the distinction matters for everything that follows: researchers separate music therapy from ordinary music listening precisely because the two can produce different results.
It comes in three broad forms. In active music therapy, patients make music alongside the therapist. In receptive music therapy, the two of them listen to it together. In what is sometimes called music medicine, music is effectively prescribed for the patient to listen to on their own.
Within those categories, therapists use a range of techniques. Group music therapy adds the benefits of socialising, since the patient works with other patients and not only with a practitioner. Improvisational music therapy treats the music itself as a conversation, with musical exchanges passing back and forth between therapist and patient.
Another technique relies on what therapists call the iso principle: starting with music that matches the patient's current mood and then gradually shifting it towards the mood you want them to reach. Therapist and patient play or listen together while the therapist adjusts the music's speed and loudness as the session goes on, often aiming to end in a calmer, more settled state.
Annie Heiderscheit and Amy Madson, writing in the journal Music Therapy Perspectives, describe the iso principle as a central method in managing mood; they trace the idea back to 1948, which makes it older than most of the evidence that now supports it.
The Case For It
Music therapy has real potential as a treatment for anxiety and depression, but like any treatment it has advantages and drawbacks. It generally carries far fewer side effects than medication, which may make it a gentler option for patients who cannot tolerate antidepressants or do not want to take them.
It may also be especially valuable for people with intellectual disabilities who struggle to communicate in words, because it offers them another way of expressing themselves. Martina de Witte and colleagues, who interviewed therapists working with adults with mild intellectual disabilities, describe how music gives a therapist a route towards reducing a patient's stress that does not depend on that patient being able to say how they feel.
On the other hand, for most people music therapy is used alongside conventional treatment such as talking therapy or medication, not instead of it, which limits how far it can stand on its own.
What the Evidence Shows
Music therapy has been linked in some studies to higher levels of serotonin, a chemical involved in regulating mood, and to lower levels of cortisol, the body's main stress hormone. Most of that evidence concerns the short term.
One of the clearest results comes from a randomised controlled trial, in which chance decides who gets the treatment, published in 2023 by Jong-In Park and colleagues in South Korea. Thirty-six children and adolescents with ADHD were split into two groups of eighteen. Both received their standard care; one group also had 24 music therapy sessions, two 50-minute sessions a week over three months.
In that group, serotonin rose and cortisol fell significantly, and scores on depression questionnaires improved, while the control group showed no significant change. It is a small trial, but it is a randomised one, and it measured hormones rather than only asking people how they felt.
A Brazilian study points the same way. Gunnar Taets and colleagues measured salivary cortisol in eighteen people being treated for drug or alcohol dependency before and after a single group music therapy session. Cortisol had fallen significantly an hour later; by two hours, it was still lower but the difference was no longer statistically significant, a useful reminder of how short the short term can be. The study also had no control group, so it cannot rule out that cortisol would have fallen anyway.
The effect is not confined to patients. Imed Kacem and colleagues offered operating theatre staff at a hospital in Sousse, Tunisia, three 30-minute music sessions each working day for a month. Afterwards, the staff reported lower perceived stress and less emotional exhaustion, one of the main components of burnout, though other measures of burnout did not change significantly.
It is worth being precise about what the study did and did not show: it measured how stressed about thirty staff said they felt, without a comparison group, and it did not measure how well anyone did their job.
Pulling the field together, a systematic review and meta-analysis led by de Witte covered 47 studies with 2,747 participants and found a medium-to-large overall effect of music therapy on stress-related outcomes. That is a substantial finding. But it is not the same as a single large trial: the size of the effect varied considerably with how each study was designed, and many small studies pointing the same way can reflect a real effect or a shared weakness in how they were done.
The Limits of the Evidence
Music therapy has been associated with reduced stress, anxiety and depression symptoms across very different groups: children and adolescents in South Korea, people in treatment for addiction in Brazil, hospital staff in Tunisia, and adolescents with depression in a small German pilot study. That breadth is encouraging. It is also, in a sense, the problem.
Most of these are small studies of very different groups, using different techniques and measuring different things, which makes them hard to compare and easy to over-read. Music therapy trials are also hard to “blind”: patients always know whether they are getting the treatment, which can colour how they report feeling. A 2024 review of the depression research by Wang and colleagues reaches a similarly qualified conclusion.
More work is needed, particularly studies that follow patients over the longer term. Almost everything that can be said confidently concerns the hours and weeks after sessions, not the years after a course of treatment. No study discussed here shows that a course of music therapy keeps someone well a year later, and until that evidence exists, the honest claim is narrower than enthusiasts tend to make.
Conclusion
For many people, music therapy combined with a conventional treatment such as psychotherapy or medication may add to the benefit of that treatment and ease symptoms, at least in the short term. It may be most distinctive for patients who struggle to communicate because of intellectual disabilities, for whom a route into therapy that does not depend on words could matter a great deal.
None of that makes music therapy a replacement for the treatments we already have, and it should not be read as one. What the evidence supports, for now, is a promising addition to them, and a reason to take a little more seriously something most of us already do by instinct when we put on a song to get through a bad day.